
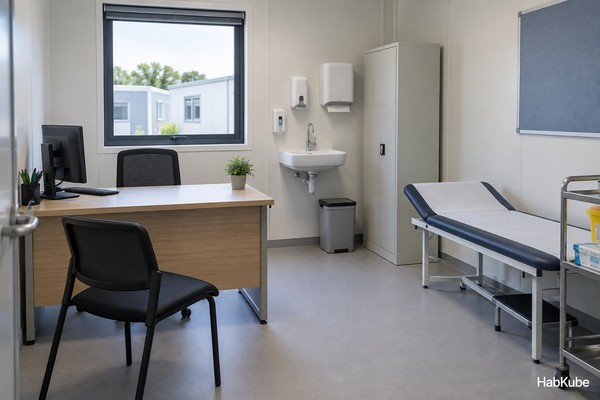
In this guide
- Define the clinical service before drawing the rooms
- Map patient, staff and service movement
- Specify surfaces and joints for the cleaning method
- Coordinate equipment, power, water and ventilation
- Connect the temporary building with the host facility
- Create an approval and commissioning responsibility map
- Review the facility against one complete patient visit
- Illustrative project review
- Build a quotation that can be evaluated line by line
- Agree factory inspection evidence for this configuration
- Coordinate shipment, installation preparation and local interfaces
- Define handover and the first operating review
- Conclusion
Procurement guidance by the HabKube project team. Examples and AI-generated images are illustrative, not documented customer deliveries or certified test results. Confirm technical and statutory requirements with qualified destination professionals.
Define the clinical service before drawing the rooms
Separate outpatient accommodation from specialist treatment capability
Write a service schedule with the healthcare operator. Identify consultation, reception, waiting, staff support, records, storage and any procedures actually planned. State what the facility will not do. A portable medical clinic for routine consultations is not automatically suitable for isolation, surgery, diagnostic imaging or inpatient care. Those functions can introduce substantially different equipment, environmental and approval requirements.
Describe patient volume and appointment patterns, including accompanying people and interpreters where relevant. Average daily visits can conceal a busy arrival window. Ask how patients register, wait, consult, receive instructions and leave. The layout should support the actual care pathway rather than merely fit a standard number of rooms inside the available module.
If the brief mentions a modular hospital ward, stop treating it as an interchangeable outpatient option. Define the care level, clinical supervision and specialist infrastructure with qualified healthcare designers. Record these decisions before inviting enclosure quotations so bidders understand what their package must support and what remains outside their competence or scope.
Map patient, staff and service movement
Review the complete visit and the back-of-house route
Place the entrance, reception and waiting functions around a realistic arrival route. Review weather protection, wayfinding, accessibility, privacy and the room available for mobility aids. Ask the destination team to establish the applicable access and egress dimensions rather than copying a generic plan from another country.
Consultation doors should not expose private conversations or examination areas to the waiting queue. Test the plan with furniture and equipment shown at their real size. Include door swings, staff movement and the space needed for cleaning. A nominal room dimension does not establish that the room works once its desk, sink, examination furniture and storage are installed.
Mark supply deliveries, cleaning materials and waste removal on the same drawing. Where the operator requires separation between flows, ask its clinical and infection-control team to define the method and boundaries. Small buildings can have significant movement conflicts; adding more rooms without reviewing circulation can reduce practical capacity instead of increasing it.
Specify surfaces and joints for the cleaning method
Review the assembled surface, not a panel label
For a prefab clinic building, ask the operator to identify the intended cleaning agents, frequency and procedures. Then review proposed wall, floor, ceiling and joinery finishes against that method. Request manufacturer information for actual products. Do not accept a broad claim of medical-grade panels without a defined property, test basis and scope.
Inspect joints, corners, floor edges, penetrations and access panels. The question is not only whether the main panel is cleanable, but whether the completed surface can be maintained without inaccessible gaps or damaged seals. Discuss replacement of a scratched finish or failed joint and whether repairs require taking an adjacent room out of service.
A modular healthcare building also needs an operating cleaning plan. Building details can assist housekeeping, but they cannot demonstrate infection-control effectiveness on their own. Use a representative corner and service penetration for a sample review, keeping the healthcare team's acceptance criteria separate from the factory's ordinary visual-finish checklist.
Coordinate equipment, power, water and ventilation
Treat each clinical device as an interface
Prepare an equipment register identifying models, dimensions, service demand and installation responsibilities. Ask who supplies and commissions each item. A power outlet shown beside a desk does not prove that electrical capacity, protection, continuity or equipment compatibility has been established for the intended clinical use.
Record handwashing locations, water interfaces, drainage routes and access for maintenance. The local engineering team should resolve water quality, hot water, backflow provisions and wastewater requirements as applicable. For ventilation, let the clinical functions and destination rules determine the specialist design. A standard comfort-cooling unit does not establish isolation performance or a controlled pressure relationship.
Coordinate penetrations before panel fabrication. Identify whether the factory provides a prepared opening, an installed component or only a drawing allowance. Reserve service access so technicians can work without unnecessarily entering a consultation space. Changes to equipment after manufacturing release should trigger a documented review of the affected room and services.
Connect the temporary building with the host facility
Confirm the operational boundary and continuity plan
A temporary medical building may support an existing clinic during renovation or operate as a separate outreach facility. These situations differ. Determine whether patients share registration, toilets, records, laboratory services, staff facilities or emergency support with another building. Show the physical route and the party responsible for keeping it operational.
Review the site during the intended operating hours. Construction traffic, dust, noise, delivery access and drainage can affect a temporary facility even when the room interior is complete. If works continue nearby, the healthcare operator and site team should agree separation, service continuity and escalation arrangements before the facility opens.
Plan interruptions and relocation explicitly. What happens if power, water or access is unavailable? Which activities stop, and who authorizes reopening? These are operator decisions, but the building specification should accommodate the agreed response. Avoid describing a transportable enclosure as instantly deployable clinical care without this supporting plan.
Create an approval and commissioning responsibility map
Release the facility against its actual service scope
List building, clinical, fire, access, electrical, plumbing and specialist approvals relevant to the destination. Give each review a responsible owner and evidence requirement. Manufacturing inspection, installation inspection and clinical commissioning are different activities. None should be treated as a substitute for the others.
Use the CDC environmental infection-control recommendations as a discussion reference with qualified healthcare personnel, not as a certificate for a cabin. Their application depends on the clinical activity and the jurisdiction. Ask the project team which requirements belong in the supplier scope and which require locally designed systems or specialist equipment.
Before handover, review the installed layout against the approved operating model. Record outstanding work, commissioning results, maintenance contacts and user training. HabKube can discuss the enclosure and manufacturing interfaces; the operator and qualified destination team must establish that the complete facility is appropriate for its clinical services.
Review the facility against one complete patient visit
Questions to resolve in the buyer decision record
Conduct a tabletop review with the operator using an ordinary appointment and a patient needing additional assistance. Start at the site entrance and continue through reception, waiting, consultation and departure. The exercise should test the approved service model, not introduce new clinical functions outside the brief.
Ask where privacy can fail, which equipment must be reached and how cleaning occurs between uses. Identify actions that depend on another building or local service. If the temporary facility shares a toilet, records system or staff support area, name that interface rather than assume proximity makes it available.
Turn unresolved observations into controlled decisions. The healthcare team determines clinical needs; the relevant designers establish technical details and local requirements; the manufacturer confirms enclosure and fit-out implications. Assign deadlines before affected details are concealed or fabricated. Keep a clear boundary between a useful mock-up review and clinical commissioning.
Finally, review the public description of the facility. A building intended for consultations should not be marketed as a fully capable hospital merely because modules can be combined. The approved service scope and specialist evidence should determine what the operator can responsibly claim. This is particularly important for portable or temporary facilities whose future location or use may change.
Project brief
Discuss the outpatient building interfaces
Share the service schedule, draft floor plan, equipment list and destination. HabKube can review enclosure and manufacturing questions alongside your qualified clinical design team.
Get a project quoteIllustrative project review
Use the example to test your own assumptions
Illustrative planning example, not a delivered HabKube clinic: an operator requests three consultation rooms during refurbishment of its permanent facility. The initial floor plan contains rooms but no equipment list or route for patients arriving from the existing reception.
The team maps the visit and discovers that one entrance conflicts with a delivery route. It revises the entrance location, protects the connection to reception and identifies which services remain in the permanent building. A device register confirms that one room needs additional power coordination. The infection-control team reviews the surface junction sample and cleaning access before production release.
The procurement package now describes an outpatient building addition with named interfaces. It does not claim that the modules provide every clinical service. That distinction helps the operator compare quotations and arrange the specialist approvals and commissioning work needed before occupation.
Build a quotation that can be evaluated line by line
For this project, the purchase brief should include outpatient functions, patient movement, privacy, equipment models, cleanable surface details, clinical engineering interfaces, shared services and the approval responsibility map. Put these facts in a numbered schedule and ask the supplier to mark each item as included, optional, excluded or awaiting a buyer decision. This makes a comparison useful even when manufacturers suggest different systems. The buying team can then see whether a lower price reflects a different material, less installation support, fewer fittings or a genuinely more efficient configuration.
Attach one controlled floor plan and a drawing register. Identify the dimensions that are fixed, the interfaces that need coordination and the assumptions that still depend on the site. If an equipment choice changes, record the replacement model and its service requirements before releasing the relevant production detail. A brief that only says “complete unit” gives purchasing, manufacturing and the destination installer too much room to interpret the same order differently.
Budget product supply, export packing, freight, local handling, site work and commissioning as separate responsibilities. Ask how a revision affects the production programme and the price basis. Agree the currency, delivery term, named place, inspection milestone and payment deliverable in the contract. The resulting comparison is a decision record the project can use after the initial commercial discussion is over.
Agree factory inspection evidence for this configuration
The factory review for this guide should focus on approved room dimensions, finish junctions, cleanable access panels, equipment allowances, service opening locations and traceability of specified materials. Translate those points into an inspection sheet with the applicable drawing revision, observation method, acceptance reference and person authorized to release the shipment. Ask to see an actual component or representative assembly where an interface matters. A photograph can show arrangement or visible finish; it cannot establish a hidden material property or an entire building performance classification.
Distinguish incoming-material checks, production checks, final inspection and specialist testing. They answer different questions and may occur at different stages. If an inspector needs to see a connection or service route before it is concealed, schedule that hold point before fabrication advances. Any test report should identify its specimen, method, conditions and limitations. Describe demonstrations accurately rather than treating a workshop demonstration as a certified result.
Keep exceptions visible. Record an observed problem, its location, the proposed correction and the evidence needed to close it. Do not approve an unresolved item simply because the shipment date is approaching. A compact evidence pack containing drawing references, relevant measurements, photographs, agreed corrections and the packing list is easier to review than a large folder of unlabeled images. Retain it with the order for receiving and future maintenance.

Coordinate shipment, installation preparation and local interfaces
Installation preparation must address patient access, separation from construction traffic, approved supports, local engineering connections and operator-led clinical commissioning. Confirm these interfaces before booking the final dispatch slot. The receiving team should know where the delivery vehicle stops, which handling equipment is available, how packages move to protected storage and which local works must be complete. A module can be finished at the factory while the destination site remains unable to receive or use it.
Match package labels to the assembly or placement sequence. Agree how loose hardware, accessories, spare parts and documents will be identified. Share package dimensions and weights with the party planning unloading; that party should select equipment and methods from the approved handling information. Store weather-sensitive items as instructed and protect exposed joints during staged assembly. Report visible transit damage with package identification and dated photographs before discarding relevant packing evidence.
Factory supply, foundations, anchoring, service connections, specialist equipment, inspections and permission to occupy may belong to different parties. Put the responsible owner beside each interface. The local team must confirm requirements for the exact use and jurisdiction, including any licensed trades or professional review. Sequence these decisions around the programme so a finished enclosure is not mistaken for an operational facility.
Define handover and the first operating review
A useful handover for this application includes approved service scope, equipment and finish registers, installation records, specialist commissioning evidence, cleaning guidance and escalation contacts. Link each record to the building or equipment identifier so the operator can find it after the installation contractor leaves. Distinguish a supply inspection from operational commissioning. The first confirms the agreed product package; the second confirms that installed systems and local interfaces function together for the intended use.
Name the person responsible for preventive checks, consumables, cleaning and replacement parts. Confirm which components can be serviced locally and which need supplier assistance. Retain finish references, component model details and installation photographs where they will help a future repair. Ask for written warranty terms and the information needed to report a concern, including exclusions and the respective responsibilities for factory components and destination work.
After the initial operating period, compare the planned workflow with what users actually do. Record recurring queues, cleaning difficulties, noise, moisture, access conflicts or maintenance delays relevant to this facility. Resolve the cause before duplicating the configuration in a later order. A planned review makes a pilot or first-phase installation valuable: it produces specific requirements for the next phase without turning an illustrative design into an unsupported performance promise.
External reference
Use the right reference for the right decision.
Clinical facilities require input from the healthcare operator, qualified designers and the relevant authorities. A modular enclosure alone does not establish clinical suitability.
Read CDC environmental infection-control recommendationsConclusion
Clarity before commitment.
Buy a clinic enclosure only after defining the care pathway and specialist interfaces. A clear scope, reviewed surface details and named approval owners make procurement more reliable. The operational facility must be assessed as a complete healthcare environment, not as a collection of manufactured rooms.
Related HabKube resources
Ready when you are
Send the clinic enclosure brief
Include room functions, finish requirements, site access and the division of specialist responsibilities. Contact info@HabKube.com for a scoped building-package discussion.
Send your requirementsCommon questions
Before you request a quote.
Can a standard office module become a clinic?+
Only after the intended services and requirements are assessed. Layout, cleanability, equipment, building services and approvals may require substantial changes. An office specification is not evidence of clinical suitability.
Is ordinary air conditioning enough?+
That depends on the clinical functions and applicable requirements. Comfort cooling alone does not demonstrate infection-control ventilation, isolation or pressure control. Have qualified clinical and engineering teams define the system.
Who approves an outpatient layout?+
The healthcare operator, qualified designers and relevant destination authorities determine the review process. Supplier approval of a manufacturing drawing does not replace clinical or statutory approval.
What information should accompany a quotation request?+
Provide the service schedule, patient-flow plan, equipment list, destination, site conditions, utility interfaces, finish requirements and responsibilities for specialist design and commissioning.